
Abstract
Materials and Methods: The patients who underwent standard of care diagnostic workup and surgery for achalasia by the same surgical team between 2007 and 2014 were recorded in a prospective database. The patients who underwent surgery as a first line treatment (Group 1, n = 55) and the patients who underwent prior ET (Group 2, n = 33) were identified. Demographic data, peroperative complications, length of hospital stay, pre- and postoperative Eckardt scores were recorded and analyzed.
Results: A total of 88 patients out of 105 were available for follow up with average follow up time of 61.9 ± 35.8 months. The mean age was 43.3 ± 15.6. Mean hospital stay was 2.3 ± 0.8 days and there was no mortality. Average duration of the effectivity of ET before myotomy was 5.7 ± 7.7 months. Peroperative complications not significantly accumulated in either group. Both groups showed comparable drop in Eckardt scores.
Conclusions: Heller myotomy and Dor fundoplication is a safe and durable option for treatment of achalasia for both treatment naive patients and patients with previous repeated ET modalities.
Introduction
Since there is a wide range of approaches available for treatment of achalasia and not a single option is firmly established as a gold standard for first choice. There is a significant subset of patients who received previous single / multiple endoscopic treatments and then referred for surgery due to the persistence of symptoms. Balloon dilatation / botulinum toxin injection can induce anatomic disruptions, loss of tissue planes, fibrosis/scar tissue around gastroesophageal junction (GEJ) and interfere with safety of standard surgical myotomy technique. We report our results of laparoscopic Heller myotomy and Dor fundoplication for patients who had previous balloon dilatation in comparison to patients who underwent surgery as a first line treatment.
Materials and Methods
88 patients were available for long term follow up. Patients were assigned into two groups as Group 1 (n=55); surgery as first line treatment, Group 2 (n=33); surgery after prior endoscopic treatment. All patients had standard workup for esophageal motility disorders (esophageal standard and/or high resolution manometry, esophagogram) and their demographic data, pre/post-operative Eckardt scores, length of hospital stays and perioperative complications were recorded.
Heller Myotomy and Dor Fundoplication was performed by the same surgical team. The operation was conducted laparoscopically with 4 port placements, typically three 5 mm trocars and one 10 mm trocar.
Data was analyzed using SPSS 11.0 software. Mann Whitney U test was used for evaluating pre and post-surgery changes in Eckardt scores, Student"s T test was used for group comparison.
Results
)
)
)
)
Table 1: Patient characteristics
Table 2: Perioperative results and outcomes
 Click Here to Zoom |
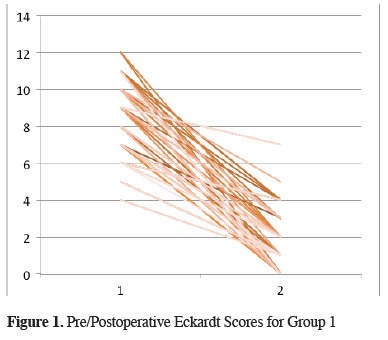
Figure 1: Pre/Postoperative Eckardt Scores for Group 1 |
 Click Here to Zoom |
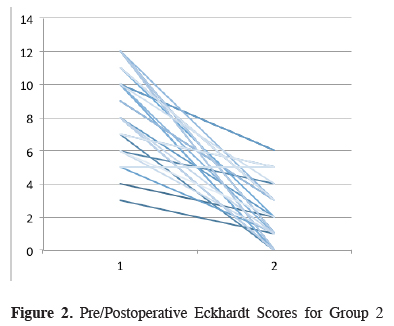
Figure 2: Pre/Postoperative Eckhardt Scores for Group 2 |
Discussion
Even though our data reveals that average duration of symptom control after an endoscopic treatment modality is close to 6 months, there is a wide range of distribution. There are studies for balloon dilatation as a first line technique and show the same pattern as well. From a clinical point, this variation in response to treatment, low morbidity and mortality and possibility of equally safe surgery after endoscopic treatment forms the rationale for a trial of endoscopic treatment as a first line option for many gastroenterologists [4]. The outcome from laparoscopic Heller myotomy is shown to be durable beyond 1 year (86% vs 76%) with very low relapse rates when compared with balloon dilatation [9]. At 2 years, a significant subset of patients (15-30%) will require symptom control for dysphagia after balloon dilatation [9,10] (Table 3).
)
Table 3: Comparison of various treatment methods for achalasia
For patients failing to respond optimally to endoscopic treatment options, referral for surgery seems to be just as safe and also a definitive solution for outflow obstruction. It results in return of peristaltic function of esophagus and potentially better long term functionality [3].
POEM also shows promising results [6], but there is no long term data available. Large case series show it to be an option comparable to surgery and caution should be exercised for patients with long standing disease and for patients who are not treatment naïve. Technical impossibility of adding an antireflux barrier procedure to POEM and already increased risk of esophageal cancer in achalasia patients may be a point of concern in the future.
In conclusion, endoscopic treatment modalities for achalasia have variable durations of symptomatic control with low risk of morbidity and do not preclude surgery for more definitive solution. Laparoscopic Heller Myotomy and Dor fundoplication results in equally favorable outcomes in both endoscopically treated and treatment naïve patients, also may provide for return of esophageal motility in long term (Table 3). POEM proponents have published encouraging results but the procedural safety itself and long term results for inability to include an anti-reflux barrier needs to be evaluated.
Declaration of conflicting interests
The author declared no conflicts of interest with respect to the authorship and/or publication of this article.
Funding
The author received no financial support for the research and/or authorship of this article.