
Abstract
Introduction
Here we report a case of a patient with complaints of hemoptysis, with an endotracheal metastasis from RCC, diagnosed by rigid bronchoscopy and palliated with APC.
Case Presentation
The lobulated and fragile endotracheal mass was resected via rigid bronchoscopy for biopsy and lumen opening under general anesthesia (Video 2). A catheter was inserted through a fiberoptic bronchoscope and APC is applied for palliation of hemoptysis. During processing, FiO2 was reduced to 21% for short periods of time (Video 3). The patient was discharged the next day with more comfortable breathing and ceased hemoptysis.
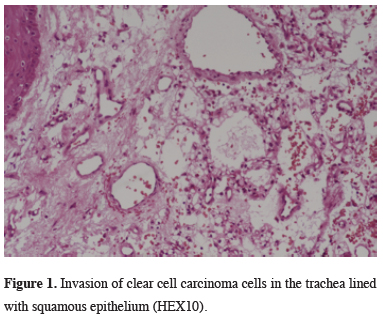
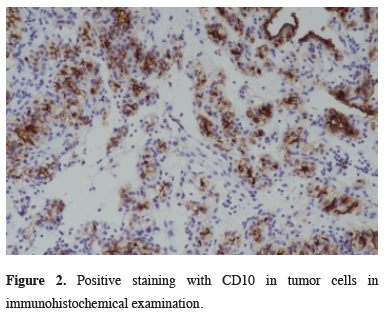
Microscopically, the tumor cells were large, the appearance of the cytoplasm clear with sharply outlined boundaries infiltrating the squamous epithelium of trachea. Immunohistochemical examination of the tumor cells showed moderate vimentin, CD10 and PAX 8 staining, and absent for TTF-1 and CK antigen staining. The morphologic and immunohistochemical features were consistent with metastatic clear type renal cell carcinoma (Figures 1,2). He was referred to the oncology clinic for appropriate systemic treatment.
)
)
 Click Here to Zoom |
Figure 1: Invasion of clear cell carcinoma cells in the trachea lined with squamous epithelium (HEX10). |
 Click Here to Zoom |
Figure 2: Positive staining with CD10 in tumor cells in immunohistochemical examination. |
Written informed consent was obtained from the patient for publication of his data.
Discussion
The most common primary sites of tumor were thyroid, esophagus and lung in the intrathoracic group whereas colorectal carcinoma, breast and melanoma metastasis were widely seen in the distant metastatic group [1,3-6]. Shavit et al reported a case of RCC metastasis of trachea the first time in 2002 [7]. In the series of 550 interventional bronchoscopic cases published by Tsuboi et al in 2016, 9 cases were RCC tracheobronchial metastases, and tracheal metastases were reported in 4 of them [8].
Renal cell carcinoma is the ninth most common cancer worldwide and accounts for 2% to 3% of all malignant tumors in adults. During the course of the disease, it metastasizes to regions such as lungs, liver, bone, brain, adrenals and lymph nodes by hematogenous route in approximately 30% of cases. Lungs are the most common target organ of RCC metastasis [2]. Although it is generally seen as bilateral parenchymal metastasis, it could be also seen as tracheobronchial metastasis in a less common way [1,3,7].
Presenting symptoms of tracheal metastases are dyspnea, stridor, cough, and hemoptysis [1,3,9]. In our patient hemoptysis was the only symptom despite the stenosis in the trachea.
Contrast-enhanced computed tomography (CT) and/or magnetic resonance imaging are important in diagnosis as they emphasize the vascular nature of the metastatic tumor. However, a small endoluminal lesion may be confused with phlegm accumulation and overlooked. Sometimes it can only be diagnosed as a metabolic activity on PET/CT, even if there is no image on CT [10].
Biopsy from the lesion provides more accurate diagnosis while risk of bleeding and airway obstruction must be kept in mind during bronchoscopy. RCC and its endobronchial metastases are frequently hypervascular and hemorrhagic tumors. Rigid bronchoscopy should be a priority in tracheal lesions because of its large working hole, allowing the use of interventional instruments, opening the tracheal lumen by taking off larger pieces, and the possibility of powerful aspiration. However, flexible bronchoscopy may also be necessary for detailed images, cleaning of the distal airways, and the use of instruments such as cryotherapy and APC. Despite all these precautions in case of abundant bleeding, it is a life-threatening situation; a surgical team and a thoracotomy set should be prepared for further operations. Inflating the cuff of the endobronchial tube over the lesion can provide a valid airway and will be a time-saving maneuver. Classical methods (ice sludge, adrenaline saline, cryotherapy, cautery, etc.) may be useful in milder hemorrhages. APC is a technique that can control bleeding instantly without penetrating into deep tissues. The coagulation is achieved with shots made without touching which also has the ability to kill tumor cells [9,11].
Since renal cell carcinoma has traditionally been defined as a radio resistant tumor, surgical excision or other methods are rather beneficial in cases of endobronchial or endotracheal metastasis. New immunotherapy agents are also applied in the treatment of metastatic renal cell carcinoma with promising perspectives [12].
In conclusion, a variety of solid malignancies may metastasize to the tracheobronchial tree. Tracheal metastasis is rare but life-threatening conditions due to tracheal stenosis and hemoptysis. Rigid and flexible bronchoscopy should be used together while the patient is under general anesthesia, and be prepared for the risk of massive bleeding. APC provides a safe hemostasis in bleeding endobronchial tumors when performed by experienced hands. Therapeutic bronchoscopy in such cases can contribute to the quality of life and may impact survival.
Declaration of conflicting interests
The authors declared no conflicts of interest with respect to the authorship and/or publication of this article.
Funding
The authors received no financial support.
Authors’ contributions
ABK, ANK: conceived and designed the current case report, co-wrote the paper, collected the clinical data. The authors discussed the case under the literature data together and constituted the final manuscript.