
Abstract
Materials and Methods: Medical records of 13 patients operated between January 2001 and July 2017, and who were diagnosed with chylothorax in the post-operative period, were retrospectively evaluated. Patients" demographic features, type of surgeries, results of histopathological examination, day of chylothorax diagnosis, and treatment results were recorded.
Results: Eight male patients (61.5%) and 5 female patients (38.5%) were included in the study. Chylothorax developed after lobectomy in 9 patients (62.23%), total pleurectomy in 2 patients (15.38%), bilobectomy in 1 patient (7.69%), and pneumonectomy in 1 patient (7.69%). Oral nutrition was discontinued immediately after chylothorax diagnosis, and patients were followed-up with parenteral nutrition. A conservative approach was used in 11 patients (84.61%). Two patients (15.39%) did not respond to medical treatment, and underwent surgery. All patients were successfully treated chylothorax.
Conclusions: Chylothorax is a rare but serious post-operative complication after thoracic surgeries. While appropriate conservative treatment leads to recovery in majority of the cases, surgery remains an important option for patients with prolonged drainage and persistent disease.
Introduction
The first striking symptom of post-operative chylothorax is the drainage of a creamy pleural fluid, which is elevated with the onset of oral nutrition [9-14]. Elevated triglyceride levels in pleural fluid (>110 mg/dL) and a cholesterol/triglyceride ratio <1 are usually sufficient for diagnosis [9-13]. The first step of treatment is to limit oral nutrition, and supplementary treatment [15]. The use of somatostatin analogs has also resulted in favorable outcomes [16,17]. Surgical treatment is still important, while percutaneous embolization techniques are considered as alternatives for treatment of patients who do not respond to medical treatment [18-20]. Here, we discuss the post-operative chylothorax cases in the last 16 years, and the treatment approaches we used. We also discuss the challenges in management of this rare but serious post-operative thoracic surgery complication.
Materials and Methods
Oral nutrition was started gradually, when the level of pleural fluid drainage decreased after appropriate medical treatment, and when the fluid was serous. The decision for discontinuing drainage was based on the appearance, volume, and biochemical analysis of pleural fluid. Drainage was discontinued when a serous pleural fluid drainage despite a fat-rich diet and a volume <100 cc per day was achieved. Prior to discharge, all patients were evaluated with chest x-rays.
Results
)
Table 1: Demographic features of patients
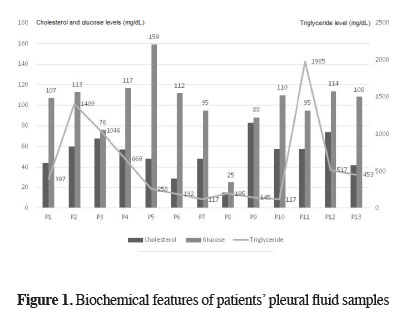
For all patients, chylothorax diagnosis was done after biochemical examination of blood and pleural fluid samples that were taken simultaneously. Biochemical analyses of pleural fluid samples showed a total protein level of 3.12 ± 0.51 (2.10-3.90) g/dL, albumin level of 1.71 ± 0.31 (1.20-2.10) g/dL, glucose level of 101.46 ± 30.08 (25-159) mg/dL, lactate dehydrogenase (LDH) level of 789.38 ± 514.50 (236-1979) U/L, cholesterol level of 52.61 ± 18.14 (15-83) mg/dL (Figure 1), and TG level of 576.92 ± 574.47 (117-1985) mg/dL (Table 2). Eight patients were diagnosed with chylothorax on day 1, 4 patients were diagnosed on day 2, and 1 patient was diagnosed on day 3. The mean time of diagnosis was post-operative 1.46 ± 0.63 (1-3) / days.
)
)
 Click Here to Zoom |
Figure 1: Biochemical features of patients" pleural fluid samples |
Table 2: Biochemical parameters in pleural fluid
Oral nutrition was discontinued immediately after chylothorax diagnosis. After consulting with gastroenterology clinic and a nutritionist, TPN was arranged for all patients. One patient was scheduled for surgery on day 4 due to a massive air leak. Air leak control and mass ligation were performed. All other patients were followed up by medical treatment. During follow-up, only 2 patients had persistent chyle drainage for >14 days. One of the patients underwent surgery for mass ligation. The other patient continued to receive medical treatment, and responded to treatment on day 21. After surgery, regression was seen in both patients. Overall, oral nutrition returned to normal on post-operative 9.61 ± 2.98 (6-21) / days. The mean duration of drainage was 13.6 ± 5.72 (7-29) / days, and the mean hospital stay was 20.46 ± 6.61 days (10-33) / days.
Three patients had secondary complications. Two patients had empyema related to prolonged drainage, and 1 patient had candida sepsis secondary to TPN infusion. Appropriate medical treatments were arranged for these 3 patients. Antibiotic treatment was discontinued when three consecutive cultures tested negative, and all patients were discharged after complete recovery. We did not observe mortality in any of the patients.
Discussion
Despite the minor differences in definition of post-operative chylothorax diagnosis, the majority of the studies consider the presence of milky pleural fluid and elevated TG levels in pleural fluid (>110 mg/dL) to be sufficient for diagnosis [8-10]. In the current study, we evaluated blood TG levels, in addition to pleural TG levels, for differential diagnosis of potential hyperlipidemia. An additional condition was to have a cholesterol/TG ratio <1 in pleural fluid.
Chyle has vital importance as it contains proteins, immunoglobulins, electrolytes, essential amino acids, and vitamins; loss of immunoglobulins results in immunosuppression, and chronic loss of chyle causes severe problems, including mortality [2,8,25]. Thus, the treatment of this condition is equally important as its diagnosis. The treatment options in the literature include algorithms that consider the level of daily drainage volume, while other studies suggest a 14-day waiting period before surgery [8,9,16,17,20]. Following chylothorax diagnosis, discontinuation of oral nutrition and replacement of chyle with appropriate parenteral treatment are considered to be the first stage of treatment [8,9,13,14]. Liu et al. [10] evaluated the volume of drainage after 4 days of medical treatment, and considered patients with a drainage volume >400 cc as candidates for surgical treatment. Those in favor of conservative treatment as the first treatment option state that surgical treatment should be chosen when conservative treatment for 14 days fails [8,26,27]. Cerfolio et al. [9] reported post-operative chylothorax development in 47 of 11,315 patients who underwent thoracic surgery. After pulmonary resection, chylothorax developed in 13 patients, and 8 patients recovered with conservative treatment. In the current study, oral nutrition was discontinued, and patients were followed-up with conservative treatment. Only 1 patient underwent surgery on day 4 due to an air leak. In case of 1 patient, surgery was performed as the patient did not respond to medical treatment. In case of 11 patients (84.61%), complete response was observed with only conservative therapy.
Another key point on chylothorax treatment is the use of somatostatin analogs. The combination of somatostatin analogs and conservative treatment has produced successful results [16,17]. In the current study, somatostatin analogs were used in only 2 patients; one of the patients underwent surgery after a 14-day waiting period. For the other patient, we did not determine a significant difference in the ending of chyle leak.
Overall, chylothorax was successfully treated with medical treatment in 11 of 13 patients, and our results are consistent with the literature. Liu et al. [10] reported chylothorax development in 20 of 776 patients (2.58%) who underwent pulmonary resection and mediastinal lymph node dissection for non-small cell lung carcinoma. In this study, 75% of the patients received conservative treatment, and 25% underwent another surgery due to chylothorax. The authors reported that the mean length of hospital stay is 19.3 days. Takuwa et al. [13] reported that 84% of patients recovered after conservative treatment. Shimizu et al. [14] showed that 81% of the patients are recovered after conservative therapy, whereas Bryant et al. [28] reported that 90% of the patients are treated with medium-chain triglyceride diet and somatostatin.
The need to perform additional procedures arises when patients do not respond to medical treatment (i.e. cases of persistent post-operative chylothorax). Embolization of thoracic duct with percutaneous methods has been suggested as an alternative revision surgery [11,18]. Surgery becomes inevitable when interventional approaches fail. Another crucial point is to locate the site of the leak. Bommart et al. [11] suggested that lipiodol lympography is a useful method to determine the leak. Alternative methods include evans blue, sudan III dye, and ingesting food (high fat or cream) mixed with sudan black dye [9,19]. In the current study, we did not use any additional method to locate the leaks. The same surgical team was responsible for revision surgeries in both early and late periods. Chyle leak was closed in both patients after operation.
Loss of immunoglobulin loss results in immunosuppression, and predisposes patients to a higher risk of opportunistic infections [8]. In the current study, empyema was detected during medical treatment of 2 patients. In another patient, candida sepsis developed secondary to parenteral nutrition. Overall, the treatment of post-operative chylothorax is a challenging process for both patients and surgeons, and requires patience. While medical treatment usually yields successful outcomes, surgical treatment may be required in certain cases. It should be kept in mind that prolonged parenteral nutrition and drainage can lead to secondary complications.
Declaration of conflicting interests
The author declared no conflicts of interest with respect to the authorship and/or publication of this article.
Funding
The author received no financial support.