
Abstract
Materials and Methods: Twenty-four, New Zealand rabbits were used in this study. The subjects are divided into three groups. All subjects’ three consecutive ribs on right hemithorax were fractured and displaced surgically. Subjects in group I were observed without any further surgical process. In group II, subjects were undergone to a second surgery process to fix the fractured two ribs by titanium plate one week after the initial operation. In group III, subjects’ three consecutive ribs were fractured and two ribs were fixed by titanium plates at the same operation session. Then subjects’ respiratory functions, survivals and health status were observed.
Results: Oxygen saturation in first week (p = 0.032), clinical survival and health status were better than the other groups in group III. Fracture healing was better in fixation groups, radiologically and clinically.
Conclusions: Early rib fixation operation is recommended for multiple displaced rib fractures to prevent secondary respiratory complications.
Introduction
The major goal in the treatment of patients with rib fractures is providing analgesia. If pain control is not optimized, complications such as atelectasis and infections are more frequently encountered [1-7]. It has been reported that, treatment options in patients with multiple rib fractures are associated with the number of fractures, location, age of the patient, and lung status [8-10]. Common indications for surgical treatment of rib fractures are flail chest, chest wall deformities / defects, pain, nonunion of fractures, symptomatic patients with three or more consecutive rib fractures [10-13].
On the other hand, surgical treatment of rib fractures is still controversial. There are numerous publications showing that early stage fixation (stabilization) is effective in preventing significant morbidities such as pain and infection in addition to a positive effect on lung function. Our clinical experience supports these findings, but there are no controlled animal experiments about this controversy. The aim of our study is to investigate effects of rib fixation surgery on respiratory functions in an experimental animal model.
Materials and Methods
Surgery
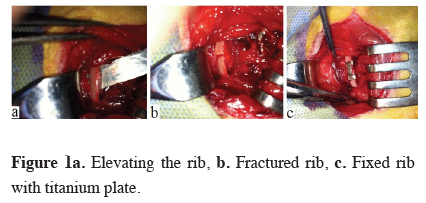
After anesthesia and endotracheal intubation, the skin and subcutaneous layers were opened while the subject was in the right side up position followed by opening the periosteum of the ribs (Figure 1a). In group I (n=8) three consecutive ribs of the subjects were surgically fractured and displaced. The subjects were observed without rib fixation surgery (Figure 1b).
In group II (n=8) three consecutive ribs of the subjects were surgically fractured and displaced. After seven days as a late fixation model, subjects were performed rib fixation surgery on two displaced ribs with titanium plaques (Figure 1c). In group III (n=8) three consecutive ribs of the subjects were surgically fractured and displaced. As an early fixation model, subjects were performed rib fixation surgery on two displaced ribs with titanium plaques, concurrently.
)
 Click Here to Zoom |
Figure 1a: Elevating the rib, b. Fractured rib, c. Fixed rib with titanium plate. |
After surgery, medical treatment; antibiotherapy (Penicillin G 50.000 U/kg) and analgesic (Flunixinmeglumin 1.1 mg/kg) were ordered to the subjects for 3 days.
The subjects were taken into the cages alone at the postoperative period. All groups were followed in terms of their weight, heart and respiratory rate, chest x-ray, complete blood count (CBC) and, arterial blood gas sampling (ABG). During the follow-up period, attention was paid for adequate food and fluid intake, appropriate ambient temperature, being away from stressor factors (intense noise, light etc.) and giving appropriate medical treatment. Daily activity levels, food and water interest and, resting postures (pain posture) were observed. The effects of fixation on respiratory functions and healing process were evaluated in the obtained data. The animals were sacrificed on 3rd week under general anesthesia.
Statistical Analysis The relationship between survival time, pre and postoperative weights, respiratory and pulse rates, saturation values, ABG and CBC parameters of the experimental groups were determined in the SPSS 15.0 package program; as well as the descriptive analyzes; Kaplan-Meier, Chi-Square and Anova tests were used. A 3-week survival analysis was performed assuming that all subjects lived at least 1 day. The results were considered statistically significant when p < 0.05.
Results
)
Table 1: Life span of subjects.
Although the average weights of subjects generally decreased, there was no significant difference between the groups at the end of the study (p = 0.280). Respiratory and pulse rates were compared, there was no significant difference between the preoperative and postoperative periods (p = 0.870 and p = 0.514 respectively). The oxygen saturation values were found better in early rib fixation group (group III) than the other two groups in first week and the difference was statistically significant (p = 0.032) (Table 2).
)
Table 2: Mean saturation levels of groups at the postopera-tive first week.
During daily follow-up, subjects in the group III were found to be more active at the early postoperative period. Daily activity, food/water interest and pain posture were better in the group III than the other two groups.
Healing of fractured ribs was followed by chest x-ray. In group I, at the third postoperative week, it was observed that fractures were not healed and there was a significant fracture line. At postoperative 7th week there was a minimal fracture healing with callus. In group III, the fixed ribs were found to heal properly without significant callus tissue in the chest x-ray even at the postoperative first week. Also it is seen that unfixed ribs healed with significant callus tissue (Figures 2a,2b).
)
 Click Here to Zoom |
Figure 2a: Fixed and unfixed ribs in x-ray, b. Significant callus tissue in chest x-ray. |
In the third group (early fixation model), the estimated life expectancy was 14.6 days; in the group II (late fixation model) the estimated life expectancy was 8.6 days; the estimated mean life span in the first group was 8.5 days.
There was no statistically significant difference between the two groups when compared with the groups Chi-square test (p = 0.750, p = 0.224, p = 0.402 respectively). However, it was accepted that the third group was clinically significant because the average life span was higher than the other groups (Table 3).
)
Table 3: Mean survival of groups in Kaplan-Meier analysis.
The subjects were followed up for daily food and water consumption. The average weight of the first group before surgery was 3230 g; second group 3133 g; the third group was identified as 3770 g. In general, all groups were found to have weight loss. At the end of the study, the average weight of the subjects in the first group was 2830 g; the average weight of the subjects in the second group was 2965 g; the average weight of the subjects in the third group was 3414 g. Weight losses calculated as grams per day and percentages, differences compared with Kruskal-Wallis test. There was no significant statistical difference between the groups (p = 0.280).
The mean saturation value of the subjects in the first group before surgery was 97%, respiratory rates 99/ min, heart pulse was detected as179/min. The mean saturation value of the subjects in the second group were 96%, respiratory rate was 139/min, pulse rate was 237/min, In the third group, the preoperative saturation values were 98%, respiratory rates were 124/min, and pulse rates were 159/min.
The clinical findings of the subjects, the saturation values and respiratory and heart pulse rates, were recorded weekly. Averages of clinical findings and differences between and within groups were assessed by One-way ANOVA and Kruskal-Wallis tests. There was no statistically significant difference between the groups (p = 0.870 and p = 0.514 respectively).
There was a significant difference between the groups only in the saturation levels at first week. In the Kruskal-Wallis test, the mean saturation levels of the third group (early fixation group) were statistically better than the other groups (p = 0.032) (Table 2).
CBC (Hgb, Hct, WBC, RBC and PLT counts) and ABG (pH, pO2, pCO2, cHCO3, cHB, sO2, cK, cNA, cCA, cGlu, cLac, cBil) analyzes of subjects were evaluated by Kruskal-Wallis and Wilcoxon tests. There was no statistically significant difference between preoperative and postoperative results (p = 0.165-1.00).
Discussion
A clinically significant result in our study was the survival of the subjects. A three-week survival analysis, in which subjects were assumed to live at least one day; mean survival in the group III (early fixation) was better than the other groups. Although survival rates were clinically significant in the group III (early rib fixation), the differences between the groups were not statistically significant (p = 0.750, p = 0.224, p = 0.402 respectively)
It was seen that the subjects in the group III returned to their normal eating and drinking habits during at the first week. They were more active, and it is observed that they had less pain than the others. We think the health status of the group III is better than the other groups. There are texts in the literature recommending rib fixation to reduce the pain of the patient if the fracture ends are moving in multiple and displaced rib fractures, even if they do not have flail chest [18].
We observed that displaced rib fractures did not heal properly due to the penetration of connective tissue between the fractured ends. This also caused a deformity in the chest wall.
There are also disagreements about the timing of the surgical treatment. Some authors performed surgical treatment within 36-48 hours after trauma, some have undergone surgical treatment on the fifth day of trauma [14,15]. But common view among authors is that surgery should not be applied when there is contusion in the lung, head trauma or major organ injury after trauma [13,19].
According to some authors, early-stage surgery causes removal of the hematoma in the fracture line and delays in fracture healing [20,21]. In a study on rabbits, it was indicated that the callus in the fractured area of the subjects which had been fixed on the 10th day after trauma was more stable [22]. However, in our study, it was observed that fracture healing was better in the early fixation group.
In conclusion, considering today’s operative techniques and minimally invasive approaches, in patients with multiple and displaced rib fractures without lung contusion and major organ injury, it is appropriate to perform rib fixation surgery before complications occur.
Declaration of conflicting interests
The authors declared no conflicts of interest with respect to the authorship and/or publication of this article.
Funding
The authors received no financial support.