
Abstract
Introduction
We present a recurrent pneumothorax case who had 5 pneumothorax episodes and one of them is during the postoperative period, diagnosed as CP.
Case Presentation
)
 Click Here to Zoom |
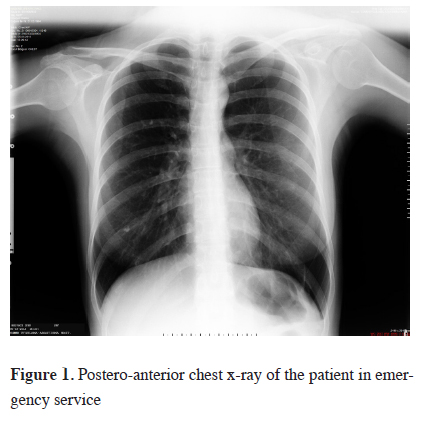
Figure 1: Postero-anterior chest x-ray of the patient in emergency service |
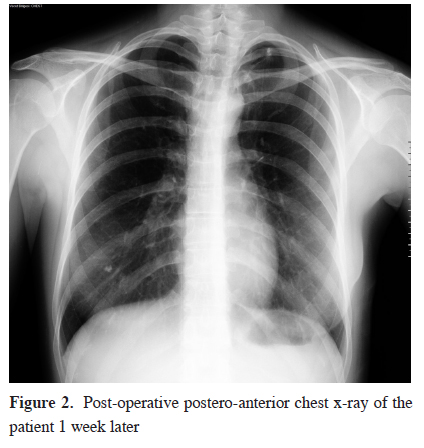
Patient was hospitalized and nasal oxygen was administered at 3 lt/min. Her pleuritic chest pain diminished and lung auscultation sounds were normal on follow-up. PA chest x-ray control revealed left lung was completely expanded and no pneumothorax was found. She was discharged on her fourth day. Her control examination 1 week later was normal. She re-admitted to our outpatient clinics approximately 3 months after her first admission with similar complaints. Her history revealed that her complaints started during menstrual period. Physical examination revealed diminished left apical lung auscultation sounds. Left sided recurrent spontaneous pneumothorax was found in PA chest x-ray. She was hospitalized again and left VATS apical wedge resection and left apical pleurectomy was performed. Neither diaphragmatic pores nor lesions compatible with thoracic endometriosis in left hemi-thorax were found during the operation. Multiple biopsies from the parietal pleura of the left hemi-thorax were performed in order to find thoracic endometriosis. Pathologic examination did not reveal endometriosis. Apical wedge resection material was also examined by pathology department and reported as bullous emphysema. Air drainage has stopped at the fourth postoperative day. Physical examination and the PA chest x-ray was normal. Thoracic drain was removed at the same day. Patient was consulted to the gynecology clinics and oral contraceptive including 2 mg of dienogest was administered. She was discharged at the fifth postoperative day. Her control examination 1 week later was normal (Figure 2).
)
 Click Here to Zoom |
Figure 2: Post-operative postero-anterior chest x-ray of the patient 1 week later |
She re-admitted to our hospital's emergency department clinics approximately 2 months after her first admission with same complaints. Her medical history revealed that she stopped taking the oral contraceptives willingly because she was planning for pregnancy. Physical examination revealed diminished left apical lung auscultation sounds. Left sided recurrent spontaneous pneumothorax was found in PA chest x-ray. Patient was hospitalized and nasal oxygen was administered at 3lt/min. Patient was consulted to the gynecology clinics and was administered oral contraceptives including 2 mg of cyproterone acetate and 0,035 mg of ethinyl estradiol. Physical examination and the PA chest x-ray at the fourth day of hospitalization was normal. She was discharged at the same day. Oral contraceptive therapy continued for 6 months because of recurrent pneumothorax. The patient is in her follow-up period for almost 2 years and she did not have a recurrent pneumothorax episode.
Discussion
In conclusion, CP causes recurrences even after the surgery. Medical treatment is successful in preventing the recurrences. Physicians should question that if the patients are taking their medical treatment regularly before deciding that the surgical treatment failed in recurrent pneumothorax.
Declaration of conflicting interests
The author declared no conflicts of interest with respect to the authorship and/or publication of this article.
Funding
The author received no financial support for the research and/or authorship of this article.