
Abstract
Introduction
Parkinson’s disease is one of the most common neurodegenerative diseases [5]. The incidence of Parkinson’s disease is increasing due to reasons such as prolongation of life span and industrialization. It is predicted that the number of Parkinson’s patients will exceed 12 million worldwide by 2040 [6]. Postural instability is an important symptom of Parkinson’s disease and may be present at the time of diagnosis; resulting in an increased risk of falling, loss of independence, and impaired quality of life [7]. Postural control is impaired in more than 75% of Parkinson’s patients, so the postural instability and the risk of falling increases [8].
In this case, we aim to emphasize that sternum insufficiency fractures may develop due to thoracic vertebral kyphosis in Parkinson’s patients.
Case Presentation
)
 Click Here to Zoom |
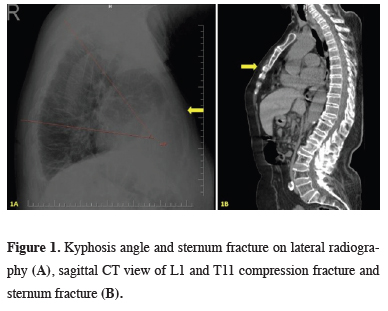
Figure 1: Kyphosis angle and sternum fracture on lateral radiography (A), sagittal CT view of L1 and T11 compression fracture and sternum fracture (B). |
Since the patient did not require surgical treatment, she was followed up in the thoracic surgery service for conservative treatment and follow-up. Bone mineral density (BMD) measurement was requested in terms of osteoporotic fracture exclusion due to the presence of kyphotic changes in T11 and L1 in the sagittal CT section (Figure 1b). The T-score in the left femur/total hip region was found to be -1.9 while the BMD value was found to be -1.7 in the lumbar region, and it was considered osteopenic. Blood D-vitamin level was 5.80, calcium was 9.05 mg/dL, alkaline phosphatase was 66 U/L and primary vitamin D deficiency was detected.
In the retrospective anamnesis of the patient, it was learned that the patient had Parkinson’s disease for 12 years and had been using pramipexole 1mg (parkipex, Generica İlaç San. ve Tic A.Ş.), domperidone 10 mg (Motilium, Johnson& Johnson), benserazide hydrochloride 125 mg (Deva Holding A.Ş.) and rasagiline 1 mg (Rasalas, Abdi Ibrahim). During the follow-up of the patient, when her tremors continued at the current drug doses, dose changes were made in consultation with the neurology and the tremors regressed. The patient was discharged with a daily dose of 1200 IU vitamin D and an appropriate analgesic treatment. She recovered without sequelae after 3 months in her follow-up. The case review was conducted according to all guidelines outlined in the Declaration of Helsinki. Written informed consent for publication was obtained from the patient and patient’s nearest relative.
Discussion
In a review published in France in 2015, it was reported that falling alone was not a risk factor for fracture in Parkinson patients. Decrease in physical activities due to loss of neuromuscular function, malnutrition, low body mass index, high parathyroid hormone, low vitamin D level, and especially the use of antiparkinsonian drugs such as L-dopa cause weakening of bone quality and atraumatic fractures [9].
Sternum fractures are more common after high-energy traumas, but they are rare. Insufficiency fractures most commonly occur in lower extremities, vertebra and pelvic bones. Sternum insufficiency fractures are extremely rare, more common in elderly patients. It is often in the manubrium zone of the sternum [3]. Our case has a manubrium sternum insufficiency fracture.
The thorax is stabilized by the ribs, sternum, and vertebrae. Insufficiency of one of these structures creates additional stress to other structures. According to Fowlers’ flexion-extension compression theory: after multiple osteoporotic thoracic vertebra compression fractures, secondary sternum insufficiency fracture may develop against flexion and compression stresses caused by chronic thoracic kyphotic deformity [1,3]. In this case, the patient had no history of previous vertebral trauma, but she had thoracic kyphosis on T11 and L1 due to compression fractures. It is thought that the patient developed secondary insufficiency fracture due to thoracic kyphosis deformity.
Sternum insufficiency fractures are divided into two as buckling or non-buckling. Buckling fractures are associated with thoracic kyphosis, while non-buckling fractures may or may not be associated with thoracic kyphosis. Our case had a buckling type sternum insufficiency fracture. With lateral chest radiographs, the localization of the sternum fracture can be determined, as well as thoracic kyphosis. CT can be used to exclude infection and malignancy [1].
In conclusion, thoracic kyphosis and sternum insufficiency fractures are associated, they are not very common. Over this rare situation, it should be considered that sternum insufficiency fracture may occur in patients with thoracic kyphosis and osteopenia after urgent cardiac and pulmonary causes are ruled out in patients admitting with anterior chest pain. Insufficiency fractures cause significant morbidity and mortality in the elderly group. Future insufficiency fractures and complications can be prevented, hospital stay times and costs can be reduced with osteoporosis treatment.
Declaration of conflicting interests
The authors declared no conflicts of interest with respect to the authorship and/or publication of this article.
Funding
The authors received no financial support.
Authors contributions
ÖO,FC; conceived and designed the current case report, co-wrote the paper, FC: collected the clinical data. The authors discussed the case under the literature data together and constituted the final manuscript.