
Abstract
Materials and Methods: Between 1994 and 2013, 1975 NSCLC patients underwent surgery in our center. The study included 774 NSCLC patients with pathological stage N0M0, and these patients were divided into 8 groups according to tumor diameter, as follows, Group 1: 0-10 mm, Group 2: 11-20 mm, Group 3: 21-30 mm, Group 4: 31-40 mm, Group 5: 41-50 mm, Group 6: 51-60 mm, Group 7: 61-70 mm, and Group 8: > 70 mm. We aimed to evaluate the prognostic effect of tumor size on overall survival and to determine a cut-off point for tumor size.
Results: The 5 year overall survival rate for groups 1 to 8 were 85.6%, 81.3%, 68.6%, 62.2%, 55%, 54.2%, 54.3%, and 45.6%, respectively. The mean follow-up time was 43.8 months. In multivariate analysis, age, tumor size, and surgical resection type had an independent prognostic value on survival.
Conclusions: Tumor size is an independent prognostic factor for pN0M0 NSCLC patients. A tumor size of 4 cm was found to be the most suitable cut-off point for survival which may be of help in decision-making for adjuvant chemotherapy.
Introduction
Materials and Methods
Results
The distribution of the patients according to tumor size was as follows, Group 1: 24 (3.1%), Group 2: 119 (15.4%), Group 3: 178 (23%), Group 4: 140 (18.1%), Group 5: 110 (14.2%), Group 6: 83 (10.8%), Group 7: 50 (6.4%), and Group 8: 70 (9%) patients. The tumor types of the patients were adenocarcinoma [374 (48.3%)], squamous cell carcinoma [393 (50.78%)] and other cell types [7 (0.9%)]. Of the patients, 522 (67.4%) underwent lobectomy, 162 (20.9%) pneumonectomy and 90 (11.63%) sublobar resection. The characteristics of the patients are summarized in Table 1.
)
Table 1: Patient characteristics
The 5 year overall survival rate for groups 1 to 8 were 85.6%, 81.3%, 68.6%, 62.2%, 55%, 54.2%, 54.3%, and 45.6%, respectively (Figure 1). Mean follow-up time was 43.8 months and median follow-up time was 43 months. Pairwise comparison between the groups for survival showed that survival was significantly longer in Group 2 than that in Group 3 (P = 0.036); the other pairwise comparisons revealed no significant difference; Group 1 vs. Group 2 (P = 0.853), Group 3 vs. Group 4 (P = 0.206), Group 4 vs. Group 5 (P = 0.088), Group 5 vs. Group 6 (P = 0.698), Group 6 vs. Group 7 (P = 0.387), and Group 7 vs. Group 8 (P = 0.305). In multivariate analysis, age, tumor diameter and resection type were found to be independent prognostic factors. Using Group 1 as reference, hazard ratios showed an increased risk for mortality, significance beginning with Group 5. As seen in Table 2 Group 3 has 1.429 and Group 4 has 2.144 times increased risk for mortality over Group 1 which are found statistically insignificant (P = 0.409, P = 0.079) but Group 5, 6, 7 and 8 have 2.910, 2.841, 2.753, 3.878 times increased risk for mortality over Group 1 and all of them are statistically significant (P = 0.015, P = 0.019, P = 0.027, P = 0.002 respectively). For resection types while pneumonectomy and lobectomy have a smiliar risk for mortality (HR = 1.045, P = 0.781), sublobar resection has 2.711 times increased risk for mortality over lobectomy (P = 0.000). We also classified patients in two groups according to tumor diameter as Group 1: ≤4 cm and Group 2: >4 cm, and found that the survival difference between the two groups was statistically significant (P = 0.000) (Figure 2).
)
)
)
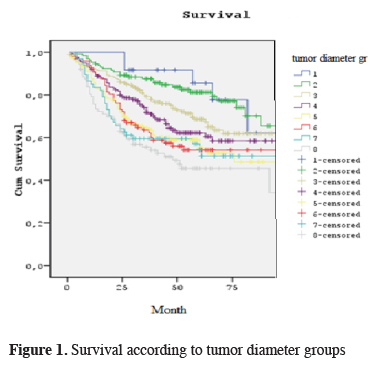
Click Here to ZoomFigure 1: Survival according to tumor diameter groups
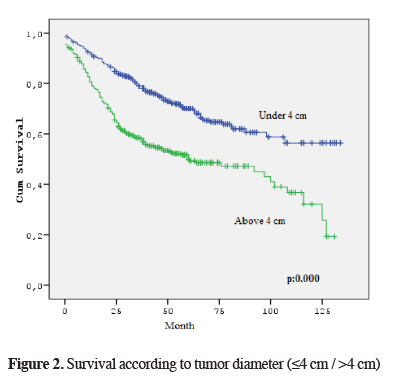
Click Here to ZoomFigure 2: Survival according to tumor diameter (≤4 cm / >4 cm)
Discussion
In our study, survival was significantly longer in Group 2 in comparison to that in Group 3 (P = 0.036). This is the 2 cm cut-off point which is used for sublobar resection [3,4]. Our study also showed that sublobar resection has a negative effect on survival compared with lobectomy in multivariate analysis (P = 0.000). These two findings cannot be combined in this study, but it seems that they are important for selecting surgical procedure also for early stage lung cancer.
In multivariate analysis, age, tumor size and surgical resection type have independent prognostic value on survival. When Group 1 was used as reference, we observed that, beginning with group 5 (41-50 mm), hazard ratios showed a significant increasing trend, and also survival difference between the groups with a tumor size ≤4cm and >4 cm was significant, showing that a tumor size of 4 cm seems to be a critical threshold. In the earlier series [5,6] this critical threshold was reported to be 5 cm but in the eight edition of TNM Rami Porta et al. [1] found 3 cm as the most significant cut-off point for T descriptor. Zhang et al. [7] studied similar patient groups and found similar results in multivariate analysis. This finding may show that adjuvant chemotherapy may be beneficial in pN0M0 NSCLC patients with tumors greater than 4 cm in size [8-10].
There are some limitations for this study. First as a prognostic factor on N0M0 patients, tumor extension is not excluded in this study, so it may be a confounding factor on survival analysis. Second, information on adjuvant chemotherapy was not available for this study.
In conclusion, for pN0M0 NSCLC patients, tumor size is an independent prognostic factor. As in the new TNM classification 1 cm increments in tumor size show a good correlation with survival. A tumor size of 4 cm is a significant cut-off point for survival which may help in giving adjuvant chemotherapy decision for N0M0 patients.
Declaration of conflicting interests
The authors declared no conflicts of interest with respect to the authorship and/or publication of this article.
Funding
The authors received no financial support for the research and/or authorship of this article.